


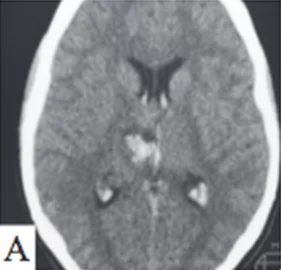
Cerebral arteriovenous malformations (AVMs) occur in approximately 0.02 % of the adult population . AVMs are diagnosed predominantly in young and middle-aged people. According to a meta-analysis, the mean age at AVM diagnosis is 33.7 years . About 10 % of all brain AVMs are located in subcortical structures — the basal ganglia, thalamus and insula.Subcortical AVMs have a more aggressive natural history than cortical AVMs, with an annual hemorrhage risk of 10–34 % and mortality of up to 62.5 %. I.G. Fleetwood et al. reported that over a 15-year follow-up period, 72 % of patients with subcortical AVMs had hemorrhage, and 86 % of patients with hemorrhage developed hemiparesis or hemiplegia. The difficulties associated with microsurgical resection of subcortical AVMs have led some surgeons to consider them “inoperable”.
Microsurgery is associated with a high risk of postoperative deterioration, especially in deep locations, whereas endovascular and/or radiosurgical treatment may achieve better clinical outcomes. Radiosurgical treatment of subcortical AVMs is associated with significant complications and a risk of rupture in the postoperative period, as well as lower obliteration rates compared with AVMs in other locations . In addition, the slow effect of radiosurgery is a limitation in treating subcortical AVMs with hemorrhagic onset, since the risk of early hemorrhage is not reduced.Several studies have compared the results of endovascular, neurosurgical and radiosurgical treatment and their combinations.
Endovascular embolization of subcortical AVMs was safer and more effective . Modern endovascular tools using embolic agents that gradually occlude the vessel lumen (Onyx 18, EV3-Covidien, Irvine, California) and flexible microcatheters allow interventional neuroradiologists to perform safe therapeutic embolization of a subcortical AVM, especially in patients at high risk of hemorrhage.


