


Patient S. S. I., 53 years old
fell ill acutely on 17.11.2022 at 9:00, when complaints of weakness in the right limbs and speech impairment suddenly appeared. His history shows that in 2010 the patient had an ischemic stroke in the territory of the left middle cerebral artery (MCA) with no signs of disability after a course of therapy and rehabilitation. He was admitted to the Center by ambulance on 17.11.2022 at 18:00 in serious condition. Neurological status on admission: NIHSS 14. Somatic status: BP – 165/90 mmHg. Brain MSCT: ASPECTs – 8. Signs of a previous ischemic stroke in the left MCA territory (a focus of post-infarction encephalomalacia in the left parietal lobe, axial size 43×23 mm).
On 17.11.2022, selective cerebral subtraction angiography was performed urgently. Tandem occlusion of the left common carotid artery (CCA) starting from its proximal segment was diagnosed (Fig. 1)

as well as occlusion of the M1-M2 segments of the left middle cerebral artery (Fig. 2). Good compensation of the left ICA territory through the anterior communicating artery from the opposite territory (Fig. 2). Collaterals ACG – 3.

Course of the operation.
Thrombosis of the left CCA at the level of an atherosclerotic plaque began 20 mm from its origin. First, balloon angioplasty of the stenosis was performed with a LOVIX 7×20 mm balloon (Fig. 3).

This made it possible to advance the VISTA BRITE TIPTM 8 F guiding catheter above the plaque. Angiographic control revealed another plaque in the middle third of the CCA with thrombosis at its level. We managed to advance a Headway 21 microcatheter over a Traxcess 0.014 microguidewire distal to the second plaque and selectively catheterize the left internal carotid artery (ICA) with it (Fig. 3, 4).

The position of the microcatheter in the ICA lumen was confirmed by superselective angiography (Fig. 5).

Over the microcatheter and microguidewire, with certain technical difficulties, we managed to advance a SOFIA PLUS 6F aspiration catheter into the lumen of the left ICA. Control angiography through the SOFIA PLUS 6F aspiration catheter confirmed thrombosis of the M1-M2 segments of the left MCA (Fig. 6).

After that, using a triaxial system (microcatheter – microguidewire – aspiration catheter), the VISTA BRITE TIPTM 8 F guiding catheter was advanced into the proximal segment of the left ICA. The aspiration catheter was brought right up to the thrombus (Fig. 7).

1 pass of direct thrombus aspiration from the M1-M2 segments of the left MCA was performed. Complete reperfusion of the left MCA territory was achieved (eTICI – 3) (Fig. 8, 9).
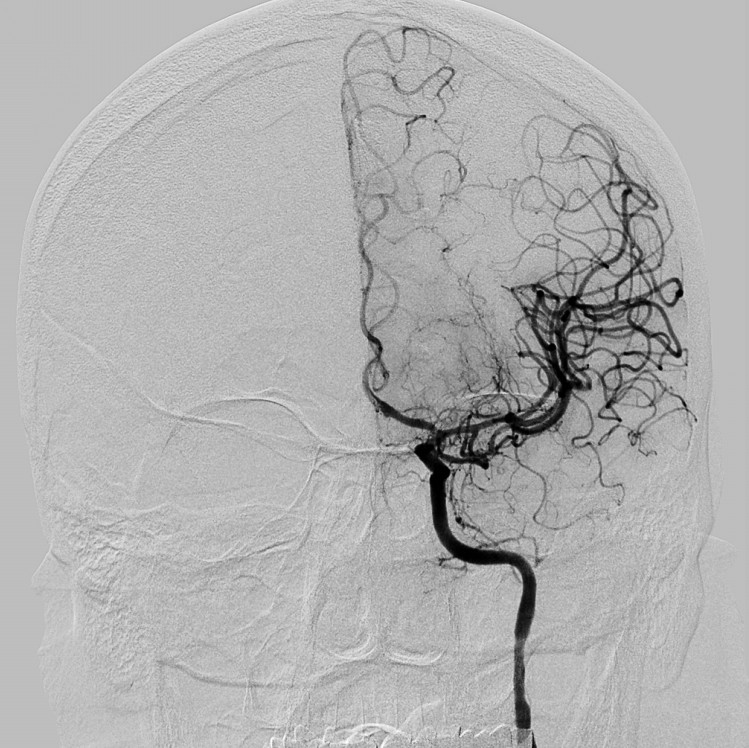
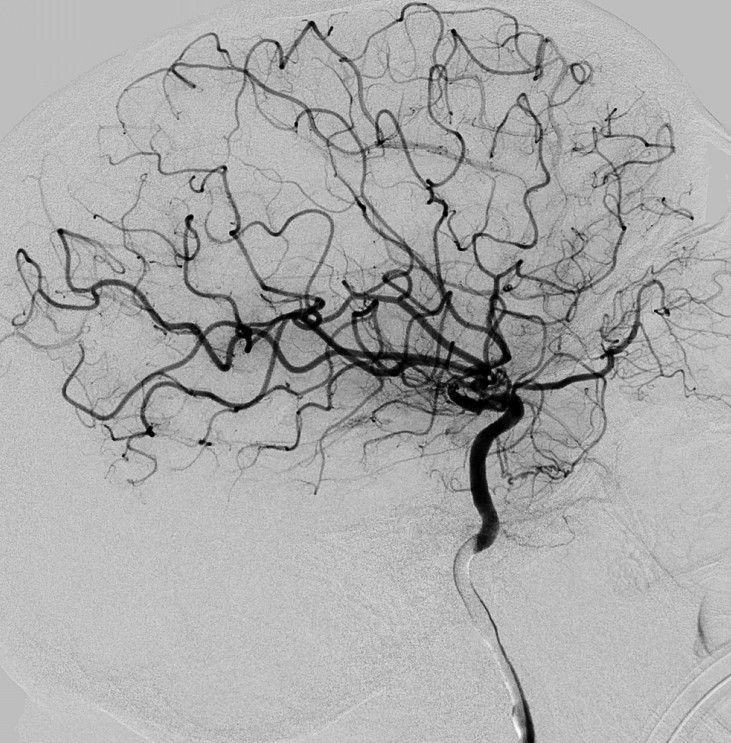
Considering the initial angiography data (good compensation of the left CCA territory through the anterior communicating artery from the contralateral territory) and the length of the affected CCA segment (more than 85 mm) (Fig. 10),

a decision was made not to restore patency of the left CCA. All instruments were withdrawn from the left CCA territory with simultaneous aspiration. After 15 minutes, angiographic control of the right carotid territory showed patency of all branches of the left MCA territory and satisfactory compensatory blood flow (Fig. 11).

Brain MSCT (control 18.11.2022) – ASPECTs – 7 (formation of an ischemic focus in the left temporo-parietal region). With conservative therapy in the neurology department at his place of residence, positive dynamics in neurological status were noted. At discharge: GCS 15, mild right-sided hemiparesis, elements of sensorimotor aphasia (NIHSS 5). For further rehabilitation, the patient was referred to a specialized rehabilitation center.
Surgeons: S.V. Konotopchyk, PhD (Med), and I.I. Al-Kashkish, PhD (Med).


